
You’ll do a urinalysis almost every shift. It takes seconds — but interpreting the colours, knowing what’s clinically significant, and understanding what to do next? That’s where students get stuck. This guide decodes every pad on the dipstick, explains common pitfalls, and gives you clear escalation rules — so you’re never guessing at the results.
Urinalysis is one of the quickest, cheapest, and most widely used tests in healthcare. It gives an instant snapshot of kidney function, hydration, infection risk, and metabolic status — all from a few millilitres of urine. Yet it’s rarely taught in depth. Lectures might mention it briefly; then you’re on the ward holding a wet stick and wondering if that pale pink means anything. The truth is: urinalysis is powerful screening — but it has limits. It guides clinical judgement; it doesn’t replace it. And some results need urgent action.
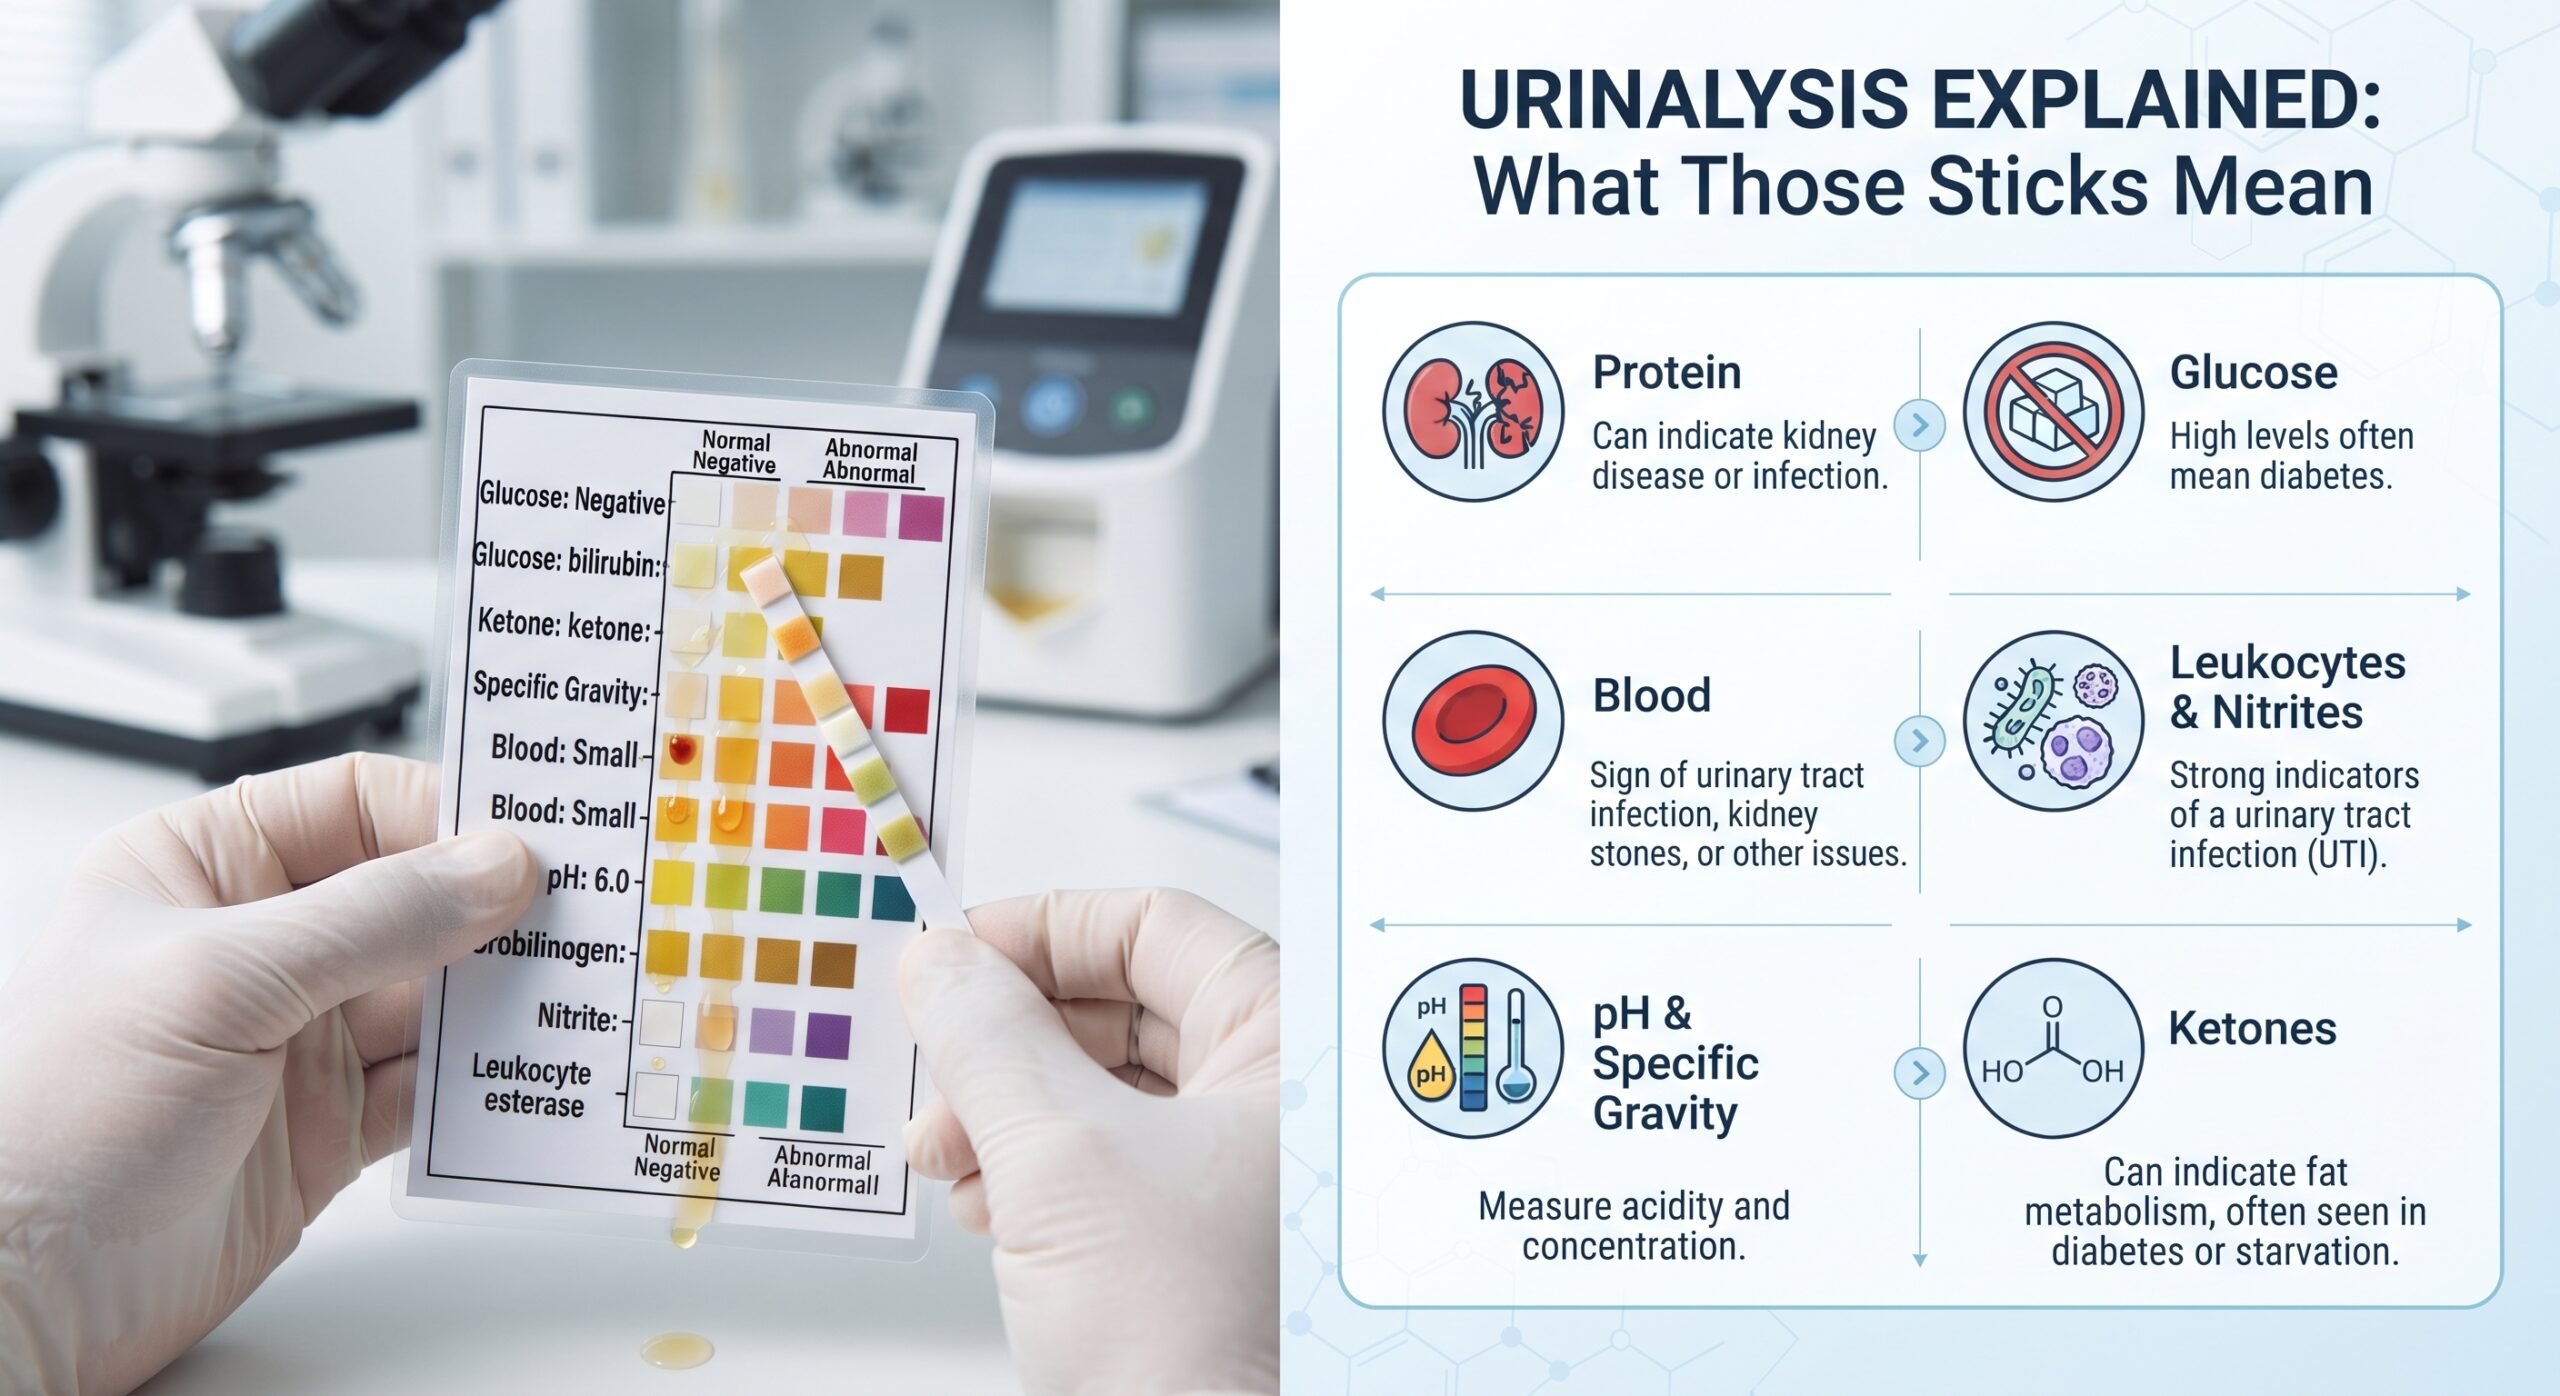
A standard urinalysis dipstick showing multiple pads. Each square tests for a different substance — compare against the chart at the correct time, and always confirm results with the clinical picture.
Part 1: Before You Dip — Correct Technique
Bad technique = misleading results. It sounds basic, but skipping these steps will give you false positives and false negatives — and that leads to unnecessary treatment or missed problems.
- Get a clean sample. Ideally a mid-stream specimen (MSU) — start voiding, collect mid-flow. This flushes away bacteria from the urethra and skin. If the patient can’t manage MSU, note that on the result — contamination is likely.
- Test promptly. Test within 1 hour of collection. If delayed, bacteria multiply, glucose drops, and pH rises — results drift. If refrigerated, bring to room temperature before testing.
- Don’t dip deep. Fully immerse the pads only — don’t soak the whole stick. Excess fluid can wash reagents from one pad to another and skew results.
- Tap off excess. Wipe the edge against the container rim or tap gently on a clean tissue — don’t drag it across.
- Read at the right time. Timing matters — usually 30–60 seconds for most pads, longer for others. Read too early = false negatives. Read too late = colours change and drift. Follow the bottle label exactly.
- Good lighting. Hold the stick flat next to the chart. Don’t hold it up against bright sunlight — it washes out the colours.
- Document immediately. Write down what you see — don’t rely on memory. Include time tested and whether sample was MSU or catheter.
⚠️ Common Mistakes That Skew Results
Leaving the stick in the urine too long — reagents leach between pads, especially protein and leukocytes. Testing old urine — false low glucose, false high pH, false positive nitrites. Not checking expiry — faded or out-of-date sticks give unreliable results. Soapy container — detergent causes false low pH and false positive protein. Always use clean, dry containers.
Part 2: The Dipstick Decoded — Every Pad Explained
Most standard sticks have 10 pads. Here’s what each one does, what’s normal, what’s abnormal, and what to do about it.
| Pad / Test | What It Detects | Normal / Negative | Abnormal — What It Means | Action & Escalation |
|---|---|---|---|---|
| Leukocytes (White Cells) | White blood cells — sign of inflammation or infection | Negative | Positive = immune response to infection or inflammation. Can be UTI, but also seen in urethritis, STI, or sterile inflammation | Escalate with symptoms (pain, frequency, fever, confusion). Send MSU for culture if positive. Note: false negatives in immunocompromised patients |
| Nitrites | Bacteria convert nitrates → nitrites in urine | Negative | Positive = bacteria present. Highly specific for UTI. False negative if urine not held in bladder ≥4 hours — morning samples most reliable | Positive = suspect UTI, send sample. Negative does NOT rule out UTI — especially in fast voids or certain bacteria |
| Blood / Haemoglobin | Red blood cells or free haemoglobin in urine | Negative or Trace | Positive = haematuria. Causes: UTI, stones, catheter, trauma, kidney disease, bladder/kidney cancer. Always investigate invisible blood | Repeat in 1–2 weeks if asymptomatic and trace. Persistent or ≥+ = refer. Urgent if visible (red/brown urine). Rule out menstruation first |
| Protein | Protein leakage from kidneys into urine | Negative or Trace | Positive = kidney damage, infection, fever, exercise, hypertension, pre-eclampsia. Persistent proteinuria needs urgent assessment | Repeat. If still positive → albumin:creatinine ratio (ACR) blood test. Pregnant = escalate immediately (pre-eclampsia risk). See below |
| Glucose | Sugar in urine — threshold ~10mmol/L blood glucose | Negative | Positive = blood glucose above renal threshold. Classic diabetes sign. Also seen in renal glycosuria (rare, non-diabetic) | Check capillary blood glucose immediately. If unknown diabetic → send bloods and refer. If known diabetic → review control |
| Ketones | Breakdown product from burning fat for energy | Negative | Positive = body lacks insulin/carbohydrate. Diabetic ketoacidosis (DKA), starvation, excessive alcohol, low-carb diets | 🚨 Moderate/Large + known diabetes = check blood ketones & blood glucose NOW. DKA is life-threatening. Escalate immediately |
| pH | Acidity or alkalinity of urine | 5.0 – 7.0 (slightly acidic) | <5 = acidic → starvation, ketosis, acidosis, diet. >7 = alkaline → UTI (urea-splitting bacteria), stasis, renal tubular acidosis | Extremes or persistent abnormal → discuss with team. Alkaline + cloudy + foul = likely UTI |
| Specific Gravity (SG) | How concentrated the urine is — measure of hydration | 1.005 – 1.030 | >1.030 = concentrated → dehydration, fluid loss, low intake. <1.005 = dilute → over-hydration, diabetes insipidus, kidney damage | High SG + dark urine → encourage fluids, monitor. Low SG + excessive thirst → investigate. Track alongside fluid balance |
| Urobilinogen | Liver/bilirubin breakdown product | Normal/Slight | Increased → liver disease, haemolytic anaemia. Decreased/absent → bile duct obstruction | Abnormal → check liver function tests (LFTs), bilirubin, full blood count |
| Bilirubin | Liver pigment — not normally in urine | Negative | Positive → liver disease or bile duct blockage. Urine may appear dark brown | 🚨 Positive = send LFTs immediately. Can indicate hepatitis, cirrhosis, gallstones, pancreatic cancer — don’t dismiss |
Part 3: Infection — When It’s UTI and When It’s Not
Urinalysis is our first clue to urinary tract infection — but it’s not definitive. Here’s how to interpret the pattern:
Typical UTI Pattern
- ✅ Leukocytes — Positive
- ✅ Nitrites — Positive
- ✅ Blood — Often Positive
- ✅ Protein — Often Trace/Positive
- ✅ pH — Often Alkaline (>7)
But UTIs can present differently — and so can other things:
- Nitrites negative, leukocytes positive — still suspect UTI. Not all bacteria make nitrites. Urine may not have been in the bladder long enough. Send sample for culture.
- Nitrites positive, leukocytes negative — rare. May be contamination or early infection. Repeat and consider culture.
- Both negative but patient has symptoms — still treat clinically. Not all infections show on sticks, especially in older adults or early stage. Trust the patient’s report.
- Positive but no symptoms — asymptomatic bacteriuria. Usually NO antibiotics needed except in pregnancy or pre-surgery. Don’t over-treat — this is a common error.
⚠️ The Elderly Patient Trap
Older adults often don’t get the classic pain/burning symptoms. Their “UTI” might present as sudden confusion, falls, incontinence, or just “not themselves.” If an older patient’s cognition changes — always dip the urine. But also: don’t blame every confusion spike on urine. Use NEWS2, check observations, and rule out other causes before treating.
Part 4: Special Cases — Pregnancy, Diabetes & Kidney Disease
Three patient groups where urinalysis carries extra weight — and extra urgency:
Pregnancy
- Protein — any amount above trace needs escalation. Could be pre-eclampsia, which endangers mother and baby. Check blood pressure immediately.
- Glucose — common in pregnancy but still needs formal glucose tolerance test to rule out gestational diabetes.
- Asymptomatic bacteriuria — MUST be treated in pregnancy. Can cause preterm labour. Positive leukocytes/nitrites = send culture and expect antibiotics.
Diabetes
- Glucose positive — confirms blood sugars are running high. Not a diagnosis on its own, but a clear warning flag.
- Ketones moderate/large — 🚨 DKA until proven otherwise. Check capillary ketones, blood glucose, and call for medical review. DKA is a medical emergency.
- Protein trace or above — early sign of diabetic kidney disease. Needs ACR test to confirm.
- UTI signs — diabetics are more prone to silent infections that progress fast. Treat promptly and monitor.
Kidney Disease / Renal Impairment
- Persistent protein — hallmark of kidney damage. Track trends, not single readings.
- Blood — needs investigation to rule out glomerular disease or stones.
- Specific Gravity fixed low — kidneys losing ability to concentrate urine. Early sign of chronic kidney disease.
- Leukocytes without nitrites — more common due to altered immune response; don’t dismiss infection.
Part 5: Urine Appearance — What Your Eyes Tell You Before You Dip
Before you even touch the stick, look at the urine. Colour and clarity give immediate clues — and sometimes urgent warnings:
| Appearance | Likely Causes | Action |
|---|---|---|
| Clear / Pale Yellow | Well hydrated — normal | Reassure |
| Dark Yellow / Amber | Concentrated — dehydration, low intake, fever | Encourage fluids, monitor intake/output, check renal function |
| Pink / Red | Blood — UTI, stones, catheter, cancer, menstruation, beetroot, certain drugs | 🚨 Rule out contamination. Always investigate new visible blood — refer to urology if persistent |
| Cloudy / Turbid + Foul Smell | Infection — white cells, bacteria, pus. Can also be phosphate crystals in alkaline urine | Send sample, start antibiotics if clinically indicated. Check hydration |
| Milky / Oily | Fat — chyluria, or pus from severe infection | Send sample urgently — rare but needs investigation |
| Brown / Black | Myoglobin (muscle breakdown — rhabdomyolysis), liver disease, old blood, some drugs | 🚨 Urgent — rhabdo can destroy kidneys. Check creatine kinase (CK), renal function, urine colour on standing |
| Orange / Brown Foaming | Bilirubin = liver disease; persistent foam = protein | Send LFTs and urine protein assessment |
Part 6: Common Pitfalls — What Can Skew the Result
Dipsticks are helpful but not perfect. Know what can give false results — and question the finding if it doesn’t fit the patient:
- Vitamin C supplements — can cause false negatives for glucose, blood, and nitrites. Very common! Ask if they take supplements.
- Antibiotics — some reduce leukocyte reaction or clear nitrites before the infection is gone.
- Contamination — vaginal discharge, menstrual blood, skin bacteria. Explain clean-catch technique properly.
- Concentrated urine — can make protein look higher than it is. Dilute sample and re-check if in doubt.
- Large volumes of fluid — dilute urine can hide low-grade infection or protein. Symptoms take priority over negative stick.
- Catheter samples — higher contamination risk. Trace blood and protein are common due to irritation. Clinical context matters more.
Part 7: Documentation & Reporting — What Goes Where
Record clearly so anyone reviewing the notes can see what you saw and what you did:
Urinalysis Documentation Checklist
- Sample type: MSU, catheter, voided, paediatric bag
- Appearance: Colour, clarity, odour
- Time tested: How long after collection
- Results: Every pad — record actual values, not just “positive”
- Action taken: Sent to lab, escalated to doctor, advised fluids, repeat test planned
- Patient symptoms: Pain, frequency, fever, confusion, nil — always note this
Example: “Urine dark yellow, clear, no odour. Tested 09:15 — MSU. SG 1.030, all other pads negative. Encouraged oral fluids. Review hydration at 12:00. Patient asymptomatic.”
Part 8: When to Send a Sample — Lab vs Dipstick
Dipsticks are rapid screening — they are NOT diagnostic. Send the urine to the lab for culture and sensitivity when:
- ✅ Leukocytes or nitrites positive — confirm organism and which antibiotic works
- ✅ Patient has symptoms but stick is negative — rule out infection
- ✅ Pregnant — any positive or suspected infection
- ✅ Elderly patient with new confusion or falls
- ✅ Blood visible or persistent trace — investigate cause
- ✅ Known recurrent UTIs — guide targeted therapy
- ✅ Catheterised patient — signs of infection
- ✅ Pre-surgery — screen for silent infection
Never rely on dipstick alone to guide long-term treatment. The lab report tells you exactly which bacteria it is and exactly which antibiotics kill it — preventing resistance and over-treatment.
Final Thought
Urinalysis looks simple — a dip, a wait, a glance. But it’s one of your most powerful daily tools. It picks up infection before the patient is acutely unwell. It flags undiagnosed diabetes. It spots kidney damage early. And it tells you when a confused older adult needs antibiotics and when they need something else entirely.
Don’t just dip and discard. Look at the urine. Think about the patient. Compare the result to what you see. And remember: the stick supports your clinical judgement — it doesn’t replace it. If something feels off — even if the stick is negative — trust your gut and escalate. That’s good nursing practice.
📚 References & Guidance
- NICE (2018, updated 2024) NG109: Urinary Tract Infection in Over 16s — Diagnosis and Management. Dipstick interpretation, when to culture, asymptomatic bacteriuria guidance.
- NICE (2019) CG182: Urinary Tract Infection in Under 16s. Dipstick limitations in children, referral thresholds.
- Royal College of Nursing (2022) Catheter Care and Urinalysis — Clinical Practice Guidelines. Standardised technique, sample collection, documentation.
- Association for Clinical Biochemistry / IBMS Best Practice in Urinalysis — Dipstick Use and Interpretation. Timing, storage, interfering substances, quality control.
- NICE (2019) NG133: Chronic Kidney Disease — Assessment and Management. Proteinuria detection, ACR testing, dipstick screening role.
- NICE (2021) NG3: Diabetes in Adults — Diagnosis and Management. Ketone testing, DKA recognition, glucose monitoring.
- NICE (2023) NG107: Hypertension in Pregnancy — Pre-eclampsia Identification. Proteinuria + blood pressure = urgent referral.
- Public Health England / NHS England Diagnostic Accuracy of Urinalysis for UTI — Evidence Briefing. Sensitivity/specificity data, false negative rates in older adults.
- National Institute for Health and Care Excellence Asymptomatic Bacteriuria — Antibiotic Stewardship Summary. When NOT to treat — key patient safety principle.
- Wilson M, et al. (2021) “Dipstick urinalysis in clinical practice: pitfalls and pearls.” British Journal of Nursing — interfering substances, timing effects, clinical correlation.
Written by: Daniel Hancock, Registered Nurse
Focus: Dipstick technique, result interpretation, UTI vs asymptomatic bacteriuria, pregnancy/diabetes/kidney flags, documentation, lab referral
Published: October 2026 | Last reviewed: October 2026
Intended for: UK student nurses — confident, safe urinalysis interpretation
Dipsticks are a screening tool, not a definitive diagnosis. Always correlate results with the patient’s symptoms, observations, and clinical history. Send samples to the laboratory for culture and sensitivity whenever infection is suspected. Vitamin C, certain medications, and sample age can all alter results. If in doubt — repeat the test or send the sample. In a deteriorating patient or suspected DKA — escalate immediately.
Build Your Daily Ward Confidence
Urinalysis is one of those skills that becomes second nature — once you know what you’re actually looking at.